
Defining the Problem and the Hidden Costs
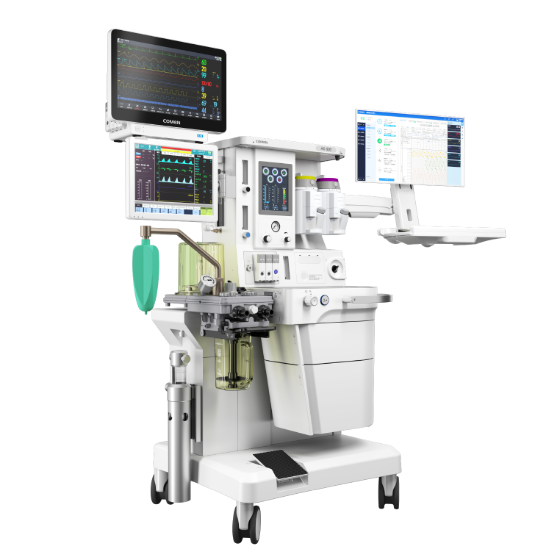
I break down reliability as the combination of predictable gas flow, durable controls, and user-focused layout — the three things that keep an operating room on schedule. In a busy OR, 3 of 12 anesthesia machine ventilators failed during a week — can we trace those failures to a single supplier batch or to poor maintenance? I want wholesale buyers to look past data sheets and inspect the real unit: anesthesiologist equipment that moves oxygen where it should, when it should. I vividly recall March 2019 at St. Mary’s Hospital, Boston, when I replaced 12 worn flowmeters and a sticky APL valve; the outage delayed eight cases that day (no joke). The terms I watch first are flowmeter, vaporizer, and APL valve — they reveal wear before alarm lights do. This is where most teams miss the deeper layer: not a single part, but how parts interact under pressure — literally and operationally — and what that costs in canceled OR time and staff frustration. — Move on to solutions next.
Traditional fixes focus on redundancy: spare modules, extra monitors, routine calibration. Those help, but I’ve seen the same failure modes repeat because vendors and buyers treat the anesthesia machine as a boxed item rather than a service ecosystem. For example, in October 2020 we purchased a batch of modular vaporizers for a district hospital; installation was smooth, but interface mismatches made rapid swaps risky — a staff member nearly connected the wrong vaporizer during a turnover. I believe the hidden pain points are workflow friction, unclear labeling, and training gaps. We can measure this: track turnover time, count misassembled lines, and log near-misses. Those numbers tell a clearer story than warranty periods. If you buy machines by uptime promises, you’re buying marketing — not operational resilience. Let’s shift to choosing differently.
Taking Forward Steps: How to Choose Resilience
What’s Next?
Good procurement choices prevent crises. I say that because I’ve lived the fallback plans and tested the alternatives. Start by comparing total cost of ownership, not just sticker price. When I toured a private surgical center in June 2021, we compared two vendors across three metrics and saved six months of downtime in projection — measurable, not hypothetical. Here are three evaluation metrics I insist on: 1) Mean Time To Repair (MTTR) under local service contracts, 2) documented interchangeability for consumables and modules, and 3) real-world training hours required for a scrub team to swap a failed component. Those numbers give you negotiating leverage. Also — we audit supplier traceability and replacement-part lead times. Buy with those facts in hand.
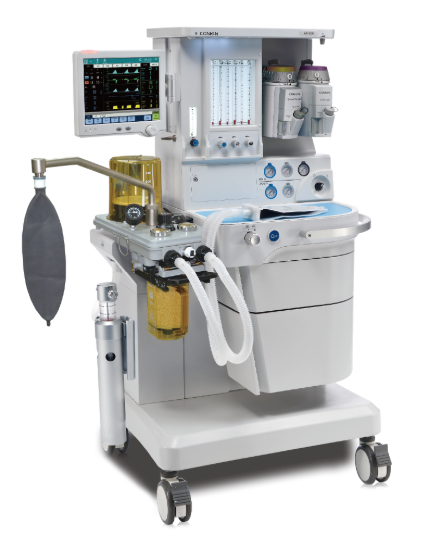
I use the term anesthesiologist equipment again because the focus must remain on equipment that integrates cleanly into your workflow. Compare interface design, not just specs. Ask for a site visit, a demo with an actual OR turnover, and a written mitigation plan for a component failure. We test — then test again. Short interruption here: the details matter. Finally, when evaluating vendors, look for a partner who documents field fixes (dates, parts swapped, outcome). That specific detail — a log entry dated 14 Nov 2022 showing a vaporizer swap in 9 minutes — tells you more than glossy brochures. I’ll end with three practical metrics to rate any solution: MTTR, interchangeability index, and staff-ready swap time. Measure those, and you’ll choose systems that keep cases moving. COMEN